ApoB explained: the cholesterol biomarker that reveals hidden heart disease risk
Learn what ApoB means, why it matters for hidden heart disease risk, and how this cholesterol biomarker adds depth to standard lipid testing.
By Aishwarya · 2 November 2026
Your cholesterol result can look reassuring and still leave an important question unanswered: how many cholesterol-carrying particles are moving through your bloodstream?
Apolipoprotein B, usually shortened to ApoB, is a key biomarker that reflects the number of lipoprotein particles most closely linked to atherosclerotic cardiovascular disease. Understanding ApoB can give you and your doctor a clearer view of cardiovascular risk, including risk that a standard cholesterol result may not show.
Before we dive into specific diseases and conditions, let’s first understand what apolipoproteins are, what role they play in the body, how to read the test results, and, most importantly, what can be done to keep the heart beating strong.
What Is Apolipoprotein B (ApoB)?
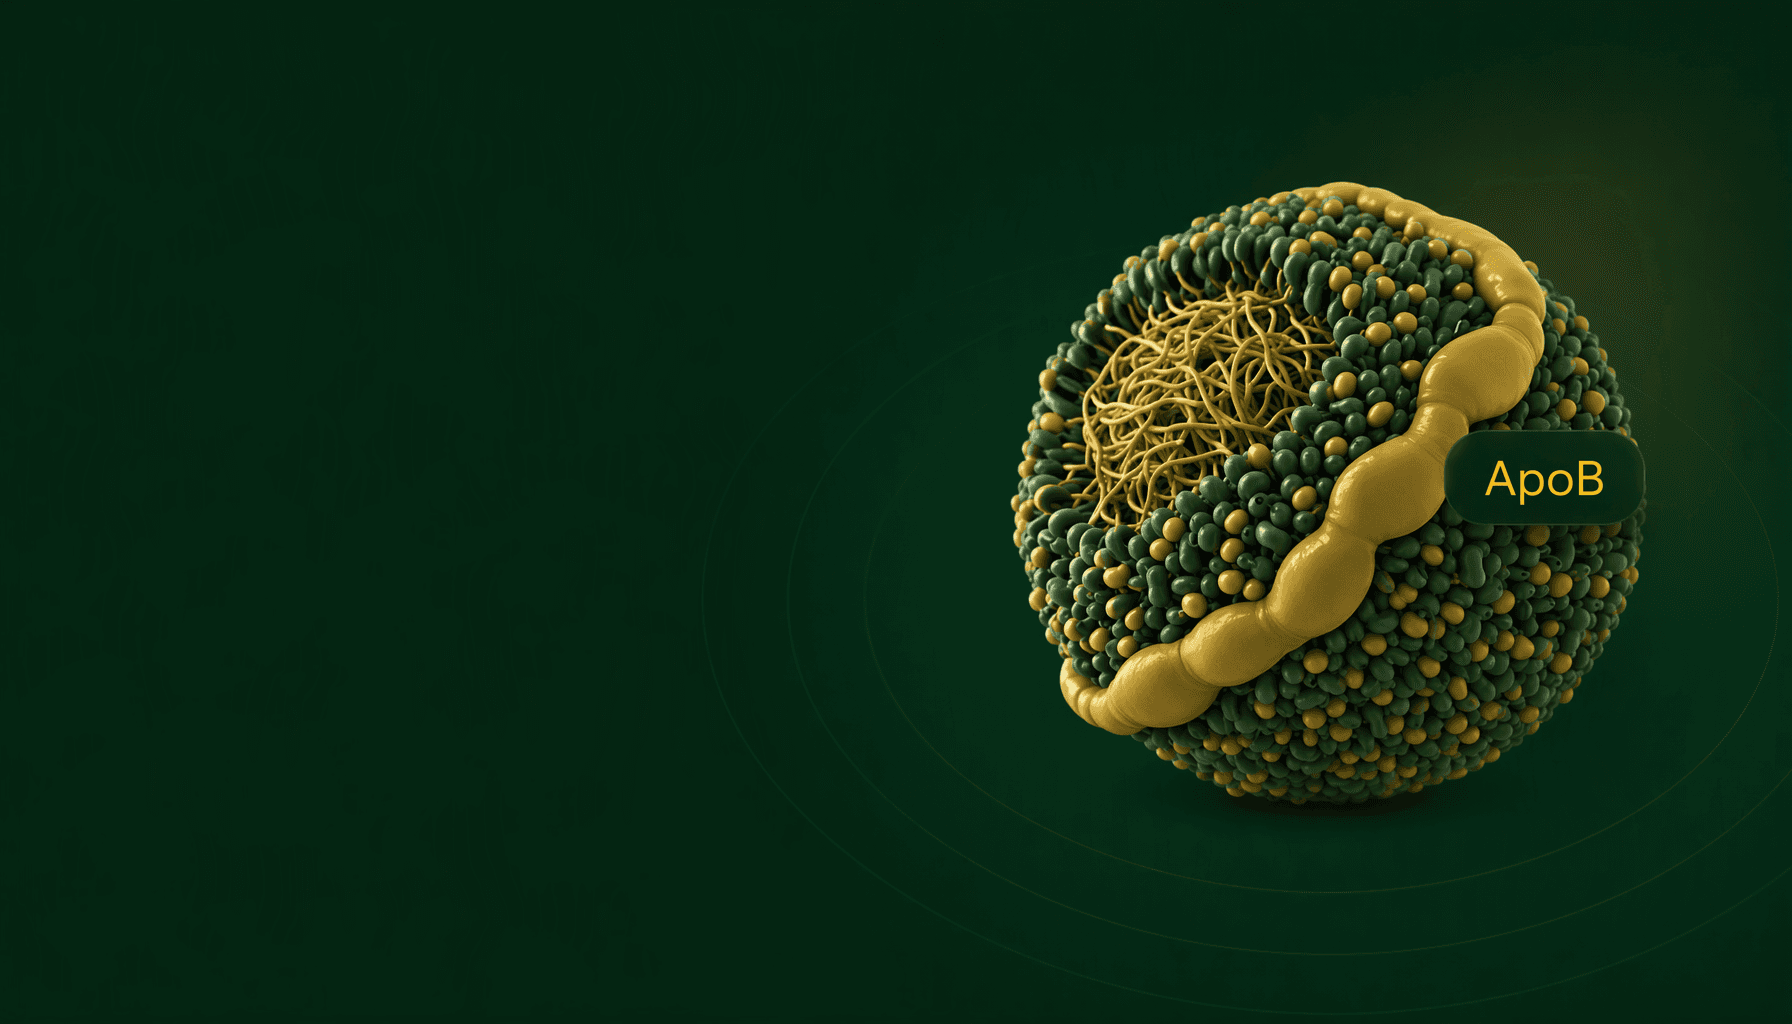
Let’s start with a fun fact. Cholesterol and triglycerides do not travel through the bloodstream independently. They are lipids, which do not dissolve easily in blood, so the body packages them inside specialised spheres called lipoprotein particles.
So, what exactly is ApoB? It is a structural protein carried by the lipoprotein particles that can contribute to atherosclerosis, a process in which particles enter and become retained in the artery wall, helping plaque develop over time.
Think of these particles as a fleet of cargo ships carrying cholesterol through your bloodstream. The major ships in this fleet include:
- LDL: Low-density lipoprotein (commonly known as “bad cholesterol”).
- VLDL & IDL: Very-low and intermediate-density lipoproteins. Some are cleared by the liver, while others are remodelled as they circulate and may eventually become LDL.
- Lipoprotein(a): An LDL-like particle with an additional protein called apolipoprotein(a). Its level is largely determined by genetics.
- Remnant particles: Cholesterol-rich particles left after triglyceride-rich lipoproteins have delivered part of their cargo.
While a standard cholesterol test measures the amount of cholesterol carried inside these particles, an ApoB test measures the concentration of ApoB and, in turn, reflects how many atherogenic particles are circulating.
An ApoB blood test is a predictive marker, not a structural scan. ApoB appears in two main forms, depending on where it is made:
ApoB48 (The Gut and Dietary Form)
- Where it is made: The small intestine.
- What it does: It acts as the structural tag for chylomicrons, which are large particles created after you eat. They transport dietary triglycerides and cholesterol from the intestine to tissues and the liver.
- Why it matters: Intact chylomicrons are generally too large to enter the artery wall. But after delivering some of their cargo, they can become smaller ApoB-48-containing remnants. Those remnants can enter the artery wall and contribute to atherosclerosis.
Your body clears many of these meal-related particles relatively quickly, but not all of them simply vanish after a fixed number of hours. Clearance varies between people and can be slower when triglyceride metabolism is disturbed.
A routine ApoB result is not a scorecard for how hard your gut worked over lunch. The test measures total ApoB in the sample. That includes ApoB-48 and ApoB-100, although ApoB-100-containing particles usually account for most of the measured ApoB.
ApoB-100 (The Liver and Heart Health Form)
- Where it is made: The liver.
- What it does: It provides the structural frame for liver-derived particles including VLDL, IDL, LDL, and lipoprotein(a). These particles carry triglycerides and cholesterol from the liver through the body.
- Why it matters: ApoB-100-containing particles can remain in circulation and become retained in artery walls. When doctors order an ApoB blood test, the result is generally dominated by ApoB-100, but the standard test measures total ApoB rather than ApoB-100 alone.
Each ApoB-containing particle carries one molecule of ApoB48 or ApoB100. Routine ApoB assays measure the concentration of total ApoB, with ApoB100-containing particles usually accounting for most of the result. ApoB concentration therefore serves as a practical proxy for the number of circulating atherogenic particles, rather than a literal laboratory count of individual particles.
Fasting is not usually required for ApoB testing, and ApoB-48 does not disappear entirely just because you have fasted. A laboratory may still ask you to fast when ApoB is being measured alongside tests that are more affected by food.
LDL cholesterol tells you how much cholesterol is being carried inside LDL particles; ApoB estimates how many atherogenic carriers are in circulation. The numbers can still look intimidating because, unless you are a clinician or deeply obsessed with this stuff, there is no obvious meaning hiding inside one isolated result. Context is what turns the number into useful information.
Other factors can increase cardiovascular risk or influence how ApoB should be interpreted:
High Blood Pressure (Hypertension): Persistently high pressure places mechanical stress on blood vessels and contributes to endothelial dysfunction, making the wider vascular environment less healthy.
Smoking and Vaping: Tobacco smoking damages the blood-vessel lining and accelerates atherosclerosis. Vaping may also affect cardiovascular health, although its long-term evidence base is not identical to that of smoking.
Diabetes / High Blood Sugar: Diabetes and insulin resistance can alter lipoprotein production, particle composition, inflammation, and blood-vessel function. ApoB needs to be read within that wider metabolic picture.
Age and Genetics: Age, inherited lipid disorders, and a family history of premature cardiovascular disease can change how strongly a doctor responds to an ApoB result.
Why ApoB Can Add Information Beyond LDL Cholesterol
Two people can have the same LDL cholesterol level but different ApoB levels. One person may have fewer cholesterol-rich particles, while the other has more particles carrying less cholesterol each. This mismatch is called discordance.
Seeing the numbers side by side helps put things in context:
Marker | What It Tells You | Main Limitation |
|---|---|---|
LDL cholesterol | How much cholesterol is carried inside LDL particles | May look acceptable (things look okay!) even when particle number is high |
Non-HDL cholesterol | Total cholesterol carried in all atherogenic particles | Measures cholesterol mass, not particle number |
ApoB | Approximate number of circulating atherogenic lipoprotein particles | It estimates the burden of atherogenic particles circulating in your bloodstream. It cannot look inside your artery walls to show whether plaque has already accumulated over the last 10, 20, or 30 years. |
Over time, that retention of particles can contribute to plaque formation, inflammation, and narrowing of the arteries.
When Should You and Your Doctor Look Deeper?
A standard cholesterol panel is useful for routine assessment, but it can miss part of the picture when cholesterol mass and particle number do not agree. ApoB may add useful context when your LDL cholesterol looks unremarkable but your metabolic health, triglycerides, medical history, or family history suggest that a closer look is warranted.
ApoB testing may be particularly useful in situations such as these:
- Metabolic and Weight Factors: Insulin resistance, metabolic syndrome, type 2 diabetes, and excess visceral fat can be associated with increased production or reduced clearance of ApoB-containing particles. The pattern varies, so none of these conditions guarantees a high ApoB result.
- High Triglycerides: Raised triglycerides can change the mix and cholesterol content of circulating particles. LDL cholesterol may therefore look acceptable even when the number of atherogenic particles is higher than expected.
- Compounding Cardiovascular Risks: High blood pressure, tobacco exposure, diabetes, and other vascular risks do not simply add another number to the report. They change the clinical context in which an ApoB result is interpreted.
- A Stubborn Family Tree: A family history of premature cardiovascular disease or a suspected inherited lipid disorder can justify looking beyond a standard lipid panel. It does not mean disease is inevitable, but it can change the level of attention needed.
- Relevant Medical Conditions: ApoB may add useful information for some people with chronic kidney disease, established cardiovascular disease, or other conditions in which treatment decisions depend on a more complete view of atherogenic particle burden.
ApoB Across Adulthood
Across broad population trends, men tend to have higher ApoB earlier in adulthood. Age, body composition, insulin sensitivity, and other metabolic factors all influence that pattern, so it is not a rule for every man and it should never replace an individual risk assessment.
For women, ApoB often rises during midlife. Research from the Study of Women’s Health Across the Nation found that ApoB increased more rapidly around the final menstrual period than in the years immediately before or after it. That does not mean every woman experiences a dramatic spike, but it does make midlife an important time to review the wider lipid pattern.
FOXO uses sex-specific laboratory reference intervals because average distributions can differ between men and women. Those intervals describe where results commonly fall; they are not the same as treatment targets. Medical decisions should still be based on overall cardiovascular risk, medical history, other biomarkers, and the clinical reason for testing.
How to Test and Interpret ApoB Levels
ApoB is measured through a blood test. The test itself does not generally require fasting, although a laboratory may ask you to fast if other markers are being measured at the same time.
One result is a snapshot. Repeat testing may be useful after a meaningful change in treatment, weight, metabolic health, or another condition that affects lipid metabolism.
How to Read ApoB Ranges
ApoB ranges can look contradictory because not every number is trying to answer the same question. A laboratory reference interval describes where results commonly fall in a tested population. A risk-based target tells a clinician how low ApoB may need to be for someone with a particular cardiovascular-risk profile.
Systems Biology and Apolipoprotein B
Your ApoB result is usually reported in milligrams per decilitre (mg/dL), but the number does not live in isolation. Its meaning changes with the rest of your lipid pattern, metabolic health, medical history, and overall cardiovascular risk. Here is how ApoB connects with some of the body’s wider systems:
Cardiovascular
A higher number of ApoB-containing particles creates more opportunities for particles to enter and become retained in artery walls. Cumulative exposure can contribute to atherosclerosis, which underlies coronary artery disease and many ischaemic strokes. ApoB indicates particle burden; it does not prove that plaque is already present.
Metabolism
ApoB cannot diagnose the metabolic problem, but it can reveal that fat transport is behaving differently. ApoB does not always turn up alone. Look around and you may also find high triglycerides, insulin resistance, increased abdominal fat, or type 2 diabetes nearby. These conditions influence how many ApoB-containing particles the liver releases and how efficiently the body removes them.
Liver and Lipoprotein Production
The liver produces ApoB100-containing VLDL particles. Insulin resistance, excess liver fat, and some inherited or secondary conditions can increase particle production or reduce clearance. ApoB reflects the number of these particles; it is not a measure of liver damage.
What’s in Your Control?
Ready for the part that matters most? You are not powerless here. Some drivers of ApoB are genetic or medical, and no amount of perfect meal prep can negotiate with DNA. But where change is possible, the point is not to live as though every good day has been cancelled. It is to build habits that make more good days possible.
Hard days will happen. They are not a verdict on your discipline; they are the days that ask you to reset and return. Good days are there to be lived. This is not a joyless trade-off. It is a practical exchange: when you care for the systems carrying you through life, you give yourself a better chance to keep doing the things that make life yours.
- Feed the Fleet Differently (Diet): Where appropriate, replace foods high in saturated fat with sources of unsaturated fat, increase soluble fibre, and favour varied, minimally processed meals. You do not need a perfect plate. You need a pattern you can return to.
- Move the Machine (Physical Activity): Regular aerobic and resistance activity supports cardiometabolic health and can improve the wider lipid pattern. The best plan is not the one that looks heroic for six days; it is the one your body, schedule, and clinician agree you can keep doing.
- Optimise the Engine (Weight & Metabolic Health): When clinically appropriate, reducing excess visceral fat can improve insulin sensitivity and may reduce the liver’s production of triglyceride-rich particles. The response varies, and body weight is never a measure of effort or character.
- Clear the Air (Tobacco & Alcohol): Avoid tobacco exposure. If you vape, discuss support for stopping with a qualified professional. Keep alcohol within clinician-advised limits, particularly when triglycerides are high.
- Look After the Full System (Related Conditions): The heart does not operate in a vacuum. Managing diabetes, blood pressure, thyroid disease, kidney disease, and other relevant conditions can improve the context in which ApoB is interpreted and treated.
- Call in the Reinforcements (Medical Care): If ApoB remains high or your overall cardiovascular risk warrants treatment, lipid-lowering medication may be appropriate. That is not a failure of willpower. It is medical care doing the job it was designed to do.
Everybody responds differently. A strong inherited tendency can keep ApoB high despite careful habits, while a metabolic change may respond to a combination of lifestyle and clinical care. What matters is finding the approach that is appropriate for your risk, your health, and your actual life.
Your result is data for a useful conversation with your doctor. It is never a judgement about your effort, discipline, or character. You do not have to become a different person overnight. You only need a next step that makes sense, and a way back when a hard day knocks you off course.
What ApoB Cannot Tell You
One number can be useful without being the final answer. ApoB needs the same honesty we ask of every biomarker: it can tell us something important, but not everything.
ApoB cannot look inside your chest to show whether plaque is already present. It cannot locate a narrowing, measure a blockage, or diagnose coronary artery disease. Those questions require clinical assessment and, when appropriate, other tests.
Its value is more focused. ApoB adds information about atherogenic particle burden to the wider cardiovascular picture. That can help you and your doctor ask better questions, interpret apparently reassuring cholesterol results more carefully, and decide whether anything needs to change.
FOXO Primer in Preventive Healthcare for ApoB Context
ApoB is one of the blood biomarkers included in FOXO Primer. FOXO reads ApoB alongside your blood and urine testing, health history, symptoms, lifestyle, and other findings to build a personalised Playbook. A FOXO Doctor reviews the Playbook and discusses what the overall pattern may mean, what deserves attention, and which next steps are appropriate. ApoB gets a seat at the table, not the entire meeting.
Explore FOXO Primer: FOXO Primer
Frequently Asked Questions
No. They are related, but they measure different things. LDL cholesterol tells you how much cholesterol is being carried inside LDL particles. ApoB reflects how many atherogenic particles are circulating, including LDL, VLDL remnants, IDL, and lipoprotein(a). One measures the cargo; the other helps estimate the number of carriers.
Yes, and this mismatch is precisely where ApoB becomes useful. You may have many particles carrying relatively little cholesterol each, allowing LDL cholesterol to look unremarkable while ApoB is elevated. This pattern is more common in people with high triglycerides, insulin resistance, metabolic syndrome, or type 2 diabetes.
No. A high ApoB result means more atherogenic particles are circulating than may be desirable for your level of cardiovascular risk. It cannot confirm that plaque or heart disease is already present. Your doctor will interpret it alongside your blood pressure, glucose levels, family history, other lipid markers, and, when appropriate, further tests.
For cardiovascular risk, fewer atherogenic particles are generally preferable, but there is no single ideal result for everyone. An unusually low result may reflect effective treatment or naturally low particle numbers. It can also occur with undernutrition, malabsorption, hyperthyroidism, severe liver disease, or rare inherited conditions, so unexpected results still deserve clinical context.
There is no universal ApoB calendar. Your doctor may repeat the test after starting or changing treatment, following a meaningful change in metabolic health, or to see whether a risk-reduction plan is working. Once results are stable, the interval should reflect your overall cardiovascular risk rather than the ApoB number alone.
Usually, yes. Eating has much less effect on ApoB than it does on markers such as triglycerides. However, your laboratory may still ask you to fast if ApoB is being measured alongside other tests, so follow the instructions provided for the full blood-test panel.
Yes. ApoB is included in the FOXO Primer blood-biomarker panel. Primer combines blood and urine testing with a detailed health and symptom history to build a personalised Playbook, which is reviewed with a FOXO Doctor. Your ApoB result is interpreted alongside your wider lipid pattern, metabolic health, and cardiovascular-risk context rather than in isolation.

Written by:
Aishwarya
I’m a content marketer at FOXO, constantly learning and writing about health, the human body and all the things we’re still figuring out about both. Outside work, I illustrate, write, research whatever has caught my attention that week, and occasionally turn those rabbit holes into projects of their own.

- Glavinovic T, Thanassoulis G, de Graaf J, et al. (2022).
Physiological bases for the superiority of apolipoprotein B over low-density lipoprotein cholesterol and non-high-density lipoprotein cholesterol as a marker of cardiovascular risk.
Journal of the American Heart Association, 11, e025858. - Johannesen CDL, Langsted A, Nordestgaard BG, Mortensen MB. (2024).
Excess apolipoprotein B and cardiovascular risk in women and men.
Journal of the American College of Cardiology, 83(23), 2262–2273. - Soffer DE, Marston NA, Maki KC, et al. (2024).
Role of apolipoprotein B in the clinical management of cardiovascular risk in adults: An Expert Clinical Consensus from the National Lipid Association.
Journal of Clinical Lipidology, 18(5), e647–e663. - Puri R, Bansal M, Mehta V, et al. (2024).
Lipid Association of India 2023 update on cardiovascular risk assessment and lipid management in Indian patients: Consensus statement IV.
Journal of Clinical Lipidology, 18(3), e351–e373. - Matthews KA, Crawford SL, Chae CU, et al. (2009).
Are changes in cardiovascular disease risk factors in midlife women due to chronological aging or to the menopausal transition?
Journal of the American College of Cardiology, 54(25), 2366–2373. - Borén J, Chapman MJ, Krauss RM, et al. (2020).
Low-density lipoproteins cause atherosclerotic cardiovascular disease: pathophysiological, genetic, and therapeutic insights.
European Heart Journal, 41(24), 2313–2330. - Ginsberg HN, Packard CJ, Chapman MJ, et al. (2021).
Triglyceride-rich lipoproteins and their remnants: metabolic insights, role in atherosclerotic cardiovascular disease, and emerging therapeutic strategies.
European Heart Journal, 42(47), 4791–4806. - Nordestgaard BG, Langsted A, Mora S, et al. (2016).
Fasting is not routinely required for determination of a lipid profile: clinical and laboratory implications.
European Heart Journal, 37(25), 1944–1958.
Disclaimer: The content on this site is for informational and educational purposes only and should not be considered a substitute for professional medical advice, diagnosis, or treatment. Always consult a qualified healthcare provider before making any changes to your health regimen, especially regarding medical conditions, treatments, or supplements. While FOXO provides science-backed insights into longevity, individual health decisions should be made in partnership with your doctor. In case of urgent health concerns, seek immediate medical attention.